
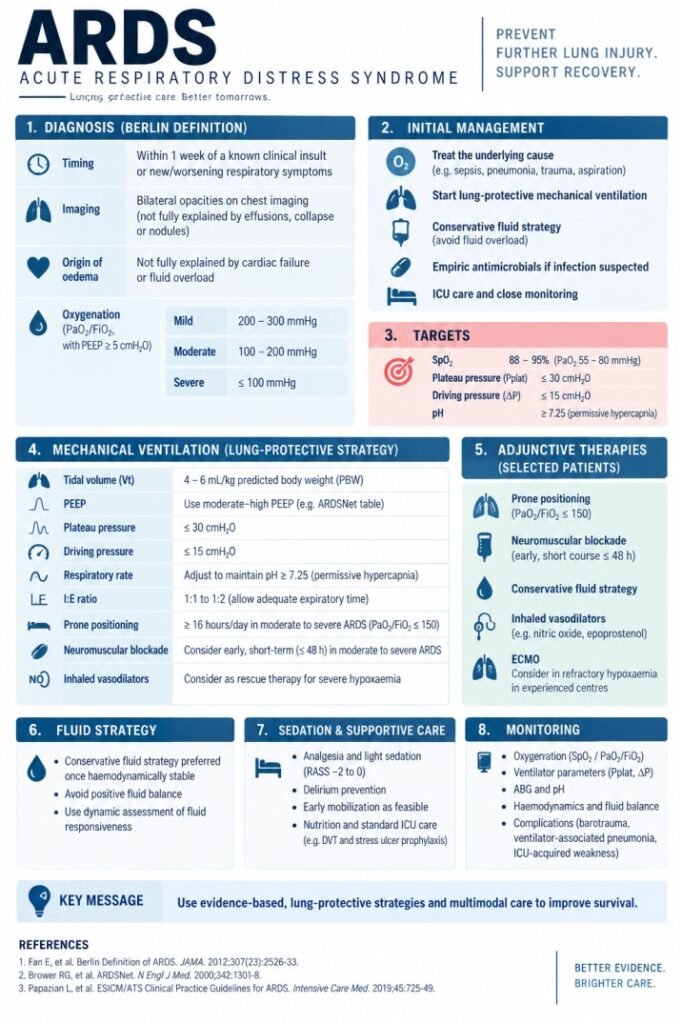
Acute Respiratory Distress Syndrome (ARDS)
ARDS (Acute Respiratory Distress Syndrome) is a diffuse inflammatory lung injury characterized by:
- Increased alveolar-capillary permeability
- Non-cardiogenic pulmonary edema
- Severe hypoxemia
- Reduced lung compliance
Leading to acute respiratory failure requiring oxygen or ventilatory support.
Table of Contents
ToggleBerlin Definition (2012) — Diagnostic Criteria
Criterion | Requirement |
Timing | Within 1 week of clinical insult or worsening respiratory symptoms |
Chest Imaging | Bilateral opacities not fully explained by effusion, collapse, or nodules,atelectasis |
Origin of edema | Respiratory failure not fully explained by cardiac failure or fluid overload or atelectasis. |
Oxygenation | PaO2/FiO2 <300 mm hg despite ≧5 cm of PEEP |
Severity Classification
Severity | PaO₂/FiO₂ |
Mild | 200–300 |
Moderate | 100–200 |
Severe | <100 |
New Global Definition of ARDS (2023)
Developed by international critical care experts led by Luciano Gattinoni and the European Society of Intensive Care Medicine task force.
Why Was a New Definition Needed?
Limitations of the Berlin Definition:
- Excluded patients on HFNC/NIV
- Required PEEP ≥5 cmH₂O
- Required arterial blood gas (PaO₂)
- Required bilateral infiltrates on chest imaging
- Poor applicability in low-resource settings
- Did not recognize “early ARDS” on noninvasive support
Criterion | Requirement |
Timing | Acute onset within 7 days of clinical insult OR new/worsening respiratory symptoms |
Imaging | Bilateral opacities on CXR, CT, or lung ultrasound(B-lines/Consolidation) |
Origin of edema | Respiratory failure not fully explained by cardiac failure or fluid overload or atelectasis. |
Oxygenation impairment | Hypoxemia with positive pressure ventilation (IMV or NIV) having PEEP/CPAP ≥5 cmH₂O OR HFNC ≥30 L/min |
If arterial blood gas unavailable:
SpO₂/FiO₂ (S/F ratio) may be used(when patient is on HFNC or or NIV/CPAP with at least 5 cm H 2 O PEEP and if Sp O 2 ≤ 97%)
Severity | SpO₂/FiO₂ |
Mild | ~235–315 |
Moderate | ~148—235 |
Severe | <148 |
- Only PaO₂/FiO₂ 201–300 mmHg with PEEP/CPAP ≥5 cm H₂O(Mild ARDS) Can be diagnosed on NIV/CPAP.
- For moderate -severe ARDS intubation Required.
Epidemiology
- Incidence: ~10% of ICU admissions
- ~23% of mechanically ventilated patients
Cause | Frequency |
Pneumonia | Most common |
Sepsis | Second most common |
Aspiration | Common |
Trauma | Frequent in surgical ICU |
Etiology
Direct Lung Injury (Pulmonary ARDS) | Indirect Lung Injury (Extrapulmonary ARDS)
|
Pneumonia (bacterial/viral/fungal) | Sepsis |
Aspiration of gastric contents | Pancreatitis |
Pulmonary contusion | Massive transfusion (TRALI) |
Near drowning | Burns |
Inhalational injury | Drug overdose |
Fat embolism | Severe trauma |
Reperfusion lung injury | Cardiopulmonary bypass |
Pathophysiology
ARDS progresses through three overlapping phases.
Exudative Phase (Day 1–7)
Histological Hallmark-Diffuse Alveolar Damage (DAD)
- Hyaline membranes
- Alveolar edema
- Neutrophilic infiltration
Mechanism | Effect |
Capillary leak | Pulmonary edema |
Surfactant dysfunction | Alveolar collapse |
Neutrophil injury | Increased permeability |
Fibrin deposition | Hyaline membrane formation |
Proliferative Phase (Day 7–21)
Repair phase involving:
- Type II pneumocyte proliferation
- Fibroblast activation
- Partial resolution of edema
Fibrotic Phase (Late ARDS)
Occurs in ~30–40% of patients.
Features:
- Interstitial fibrosis
- Pulmonary hypertension
- Severe reduction in lung compliance
Pathophysiology | Details |
Shunt Physiology (Major Mechanism of Hypoxemia) | The dominant mechanism of hypoxemia in ARDS. Alveoli are filled with fluid, inflammatory exudate, or collapsed, while pulmonary perfusion continues. Blood passes through non-ventilated alveoli, resulting in a true intrapulmonary shunt that is often poorly responsive to oxygen therapy. |
V/Q Mismatch | Some lung regions have poor ventilation but preserved perfusion, leading to ventilation-perfusion mismatch. This contributes to hypoxemia in addition to shunt physiology. |
Reduced Lung Compliance | The ARDS lung becomes stiff and difficult to inflate. Causes include alveolar edema, atelectasis (alveolar collapse), and later fibrosis. Increased lung stiffness results in higher work of breathing and increased ventilatory pressures. |
Pulmonary Hypertension | Common in moderate-to-severe ARDS. Mechanisms include hypoxic pulmonary vasoconstriction, pulmonary microthrombi, endothelial injury, and vascular remodeling, leading to increased pulmonary vascular resistance and right ventricular strain. |
ARDS Lung Mechanics (“Baby Lung Concept”) | Introduced by Luciano Gattinoni. The functional lung available for ventilation is markedly reduced, resembling the size of a “baby lung.” Only a small portion of the lung remains aerated and available for gas exchange. Consequently, normal tidal volumes may overdistend the remaining healthy alveoli, causing ventilator-induced lung injury (VILI). This concept forms the basis for low tidal volume ventilation (≈6 mL/kg predicted body weight) in ARDS. |
Clinical Features
Symptoms
- Dyspnea
- Tachypnea
- Hypoxemia
Signs
Finding | Explanation |
Tachypnea | Respiratory distress |
Diffuse crackles | Alveolar edema |
Cyanosis | Severe hypoxemia |
Accessory muscle use | Increased work of breathing |
Investigations
Do All possible investigations relevant to history to find out cause of ARDS,Finding out cause has paramount importance!!
- CBC
- Blood cultures.
- Nasopharyngeal PCR for influenza, COVID-19 etc
- Sputum culture & staining
- Urine Culture, Urine Antigen
- Procalcitonin, C-reactive protein.
- If suspected Fungal Assessment
Arterial Blood Gas
Early:Respiratory alkalosis
Late:Severe hypoxemia—Possible respiratory acidosis
Chest X-ray
- Bilateral diffuse infiltrates
- “White lung”
CT Scan(Gold standard imaging)
Region | Appearance |
Dependent lung | Consolidation |
Nondependent lung | Ground glass |
Aerated lung | “Baby lung” |
Lung Ultrasound
- Cardiogenic pulmonary edema: B-lines distributed throughout the lung, pleural effusions, pleural line is normal (thin).
- ARDS: patchy areas with B-lines intermixed with areas with A-lines (normal lung),pleural line may appear thick/ragged.
Hemodynamic Assessment
To exclude cardiogenic edema.Methods:
- Echocardiography
- Pulmonary artery catheter (rarely used)
Differential Diagnosis
Condition | Distinguishing Feature |
Cardiogenic pulmonary edema | Elevated PCWP |
Diffuse alveolar hemorrhage | Hemoptysis |
Acute interstitial pneumonia | Idiopathic |
Pulmonary vasculitis | Autoimmune markers |
Management
- Lung Protective Ventilation
- Established by the ARDSNet ARMA Trial.
- No ventilator mode has been proven superior.The priority is lung-protective ventilation, not the specific mode.
- Volume Assist-Control (VC-CMV / VC-AC)—Most commonly used mode in ARDS trials
Predicted Body Weight Formula
- Male:PBW = 50 + 0.91(height cm − 152.4)
- Female:PBW = 45.5 + 0.91(height − 152.4)
Parameter | Target |
Tidal volume | 4–6 mL/kg PBW if could not tolerate then May increase to 8 cc/kg if plateau <30 cm |
Plateau pressure | <30 cmH₂O |
Driving pressure | <15 cmH₂O |
PEEP | Moderate–high |
SpO₂:
| 88–95%
|
PaO₂: | 55–80 mmHg |
pH | >7.2 |
respiratory rate (RR) | 35 bpm(maximum) |
inspiratory-to-expiratory time ratio | less than 1 |
What about Peak Pressure?-Although not guideline-mandated:
- Ppeak <35–40 cmH₂O is commonly accepted.
- If Ppeak >40–45 cmH₂O, investigate:Secretions—Bronchospasm—ETT obstruction—Pneumothorax—Excessive tidal volume—Excessive PEEP
The key question is always:What is the plateau pressure?
Peak airway pressure has no specific guideline limit because it is heavily influenced by airway resistance and does not reliably reflect alveolar overdistension.
PEEP Strategy
Purpose:Prevent alveolar collapse —Reduce atelectrauma—Reduce FiO₂ requirement—Achieve lung recruitment safely—Improve oxygenation—Reduce shunt fraction
Evidence for High vs Low PEEP
Major trials:ALVEOLI,LOVS,EXPRESS
Findings:
- No major mortality benefit overall
- Moderate-severe ARDS may benefit from higher PEEP
- Better oxygenation and fewer rescue therapies
Methods to Set Optimal PEEP
Optimal PEEP -The PEEP at which Driving pressure is lowest or Changes minimally despite increasing PEEP.Best physiologic marker of optimal PEEP = Highest compliance (lowest elastance)
1. ARDSNet PEEP-FiO₂ Table
Disadvantages:Can not be applicable to focal ARDS(this can be check by chest X-ray pathology is focal or not)
2. Compliance Method
- Increase PEEP gradually and identify best compliance.
- Compliance improves with recruitment but worsens with overdistension.
- Optimal PEEP:Highest static compliance
- Static compliance formula: Cstat =(Pplat −PEEP)/VT
- Higher compliance suggests better recruitment without excessive overdistension.
3. Driving Pressure Guided PEEP
- Driving pressure:ΔP=Pplat −PEEP
- Goal:Keep driving pressure < 15 cm H₂O
- Lower driving pressure associated with improved survival.
- If increasing PEEP:
- Decreases driving pressure → beneficial recruitment
- Increases driving pressure → overdistension likely
Example:Before recruitment
- PEEP = 8 and Pplat = 24 and Driving pressure = 16
After increasing PEEP:PEEP = 12,Pplat = 25 but Driving pressure = 13(Driving pressure falls → recruitment occurred → beneficial.)
4. Pressure-Volume Curve Method
- Identify:Lower inflection point (LIP) and Upper inflection point
- Set PEEP: Slightly above LIP
- Limitations: In ARDS, lung recruitment (opening of collapsed alveoli) does not occur only at the lower inflection point of the pressure-volume curve. Instead, alveoli may continue to open throughout the entire curve, even at pressures above the upper inflection point.At the same time, some already-open alveoli may become overdistended (overstretched), leading to hyperinflation, which is commonly seen on CT scans.
5. Esophageal Pressure Guided PEEP
- Uses esophageal balloon to estimate pleural pressure.
- Transpulmonary pressure:PL =Paw −Ppl
Useful in:
- Obesity
- Elevated abdominal pressure
- Severe ARDS
Goal:End-expiratory transpulmonary pressure around 0–5 cm H₂O
Disadvantage-Unfortunately, a larger follow-up multicenter
randomized trial of esophageal pressure–directed PEEP for patients with moderate-to-severe ARDS failed to demonstrate a difference of mortality or ventilator free days compared with conventional PEEP titration strategies.
Other Ventilation Modes
High-Frequency Oscillatory Ventilation(HFOV)
Trials:OSCILLATE,OSCAR Results:No benefit,Possible harm
Airway Pressure Release Ventilation (APRV)
it is an alternative invasive mechanical-ventilation strategy for ARDS. Its theoretical advantage is maintaining a relatively high continuous airway pressure for most of the respiratory cycle, with brief pressure releases to allow CO₂ removal, while permitting spontaneous breathing.—No proven mortality benefit but improvements in ventilator-free days, extubation, and hemodynamics
Best candidates for APRV
- ARDS with substantial dependent/posterior atelectasis or recruitable lung
- APRV’s prolonged high-pressure phase may help maintain recruitment.
- Patients who cannot undergo prone positioning
- APRV may be considered when proning is contraindicated or not feasible.
- Morbidly obese patients with significant atelectasis
- Higher mean airway pressure may be useful because obesity increases pleural pressure and promotes dependent lung collapse.
- However, obesity alone is not an indication for APRV.
- Patients with difficult-to-control respiratory drive
- APRV may be useful when maintaining spontaneous breathing is desirable and deep sedation/neuromuscular blockade is problematic.
- However, excessive spontaneous effort can increase transpulmonary pressure and potentially contribute to P-SILI.
Permissive Hypercapnia
- Allowed in ARDS ventilation.
- Reason:Low tidal volume leads to CO₂ retention.
- Acceptable:pH ≥ 7.20
- IV bicarbonate can be used to treat low pH
- Contraindications of Permissive Hypercapnia :
- Raised ICP
- Severe pulmonary hypertension
- Pregnancy(relative contraindication)
Prone Positioning
- Supported by the PROSEVA Trial
- Consider after >12 hours of ventilator optimization to rule out patients with pseudoARDS(Atelactasis)
- Indication:PaO₂/FiO₂ <150
- Protocol:≥16 hours/day
Effect | Mechanism |
Improves oxygenation | Better V/Q matching |
Reduces mortality | Lung recruitment |
Improves secretion clearance | Drainage |
Proning can be stopped if the patient is able to maintain a PaO2/FiO2 ratio >150 mm with an FiO2 ≤0.6, at least four hours after supination.
Neuromuscular Blockade
Used early in severe ARDS.during the first 48 hours
Evidence:ACURASYS Trial
Drug:Cisatracurium infusion (48 hrs)
Benefits:
- Reduced ventilator asynchrony
- Improved oxygenation
For ventilator Asynchrony Use Propofol/ketamine/fentanyl.
Corticosteroids
- Consider if PaO2/FiO2 <200 mm hg & no contraindication(active fungal or mycobacterial infection).
- Benefit when <7 days after admission
- DEXA-ARDS trial utilized 20 mg dexamethasone for 5 days, followed by 10 mg dexamethasone for 5 days (or discontinuation before 10 days, if the patient was extubated).
- SCCM/ESICM guidelines recommend methylprednisolone 1 mg/kg/day, with a gradual taper over 14 days.
- Benefits:Reduced ventilation duration,Possible mortality reduction
Fluid Strategy
- Trial: FACTT Trial
- Approach:Restrict fluid strategy after initial stabilization,can Use diuretics
- Benefits:Shorter ventilation duration
Parameter | Target |
Daily balance | 0 to -500 mL/day |
CVP | <4-8 mmHg |
PAOP (if PAC used) | <8 mmHg |
EVLW (PiCCO) | Reduce progressively |
Lung ultrasound | Decreasing B-lines |
Assess Fluid Responsiveness Before Giving Fluids
Static measures such as CVP are poor predictors.
Prefer dynamic indices:
Test | Positive Response |
Passive Leg Raise | ↑ SV >10% |
Stroke Volume Variation | >12-13% |
Pulse Pressure Variation | >13% |
Echocardiography | ↑ VTI >10-15% |
Mini-fluid challenge | SV increase |
Only give fluid if responsive.
Type of Fluids
Preferred Balanced Crystalloids
- Ringer Lactate
- Plasma-Lyte
Advantages:
- Less hyperchloremia
- Less renal vasoconstriction
ECMO
Used in refractory hypoxemia.
Evidence: EOLIA Trial
Indications:
Parameter | Threshold |
PaO₂/FiO₂ | <50 for >3 hrs |
PaO₂/FiO₂ | <80 for >6 hrs |
pH | <7.25 with PaCO₂ >60 |
Type:VV ECMO
Recruitment Maneuvers
Transient increase in airway pressure.
Examples:
- Sustained inflation(PEEP 35–45 cmH₂O and Sustained inflation 30–60 sec)
- Staircase recruitment
Evidence: uncertain benefit(RMs can neither be recommended nor discouraged for all patients, but can be considered on an individualized basis for patients with life-threatening hypoxemia.)
Stress Index
Used during volume-controlled ventilation.
Evaluates the shape of the inspiratory pressure-time curve.
Interpretation
Stress Index | Meaning |
|
<1 | Tidal recruitment/collapse | Pressure curve bends downward—More alveoli opening during inspiration .Under-recruitment
|
1 | Optimal inflation | Straight line-Meaning:
|
>1 | Overdistension | Pressure curve bends upward
|
Mechanical Power
Definition-Total energy transferred from ventilator to lung per minute.Represents cumulative risk of VILI.
Components
Mechanical power integrates:
- Tidal volume
- Respiratory rate
- Driving pressure
- PEEP
- Flow
- Airway pressure
into a single variable.
Simplified Formula (Volume Control)
MP=0.098×RR×VT×(Ppeak −0.5×ΔP)
Where:
- MP = Mechanical Power (J/min)
- RR = Respiratory Rate
- VT = Tidal Volume (L)
- ΔP = Driving Pressure
Interpretation
Mechanical Power | Risk |
<12 J/min | Lower VILI risk |
12–17 J/min | Intermediate |
>17 J/min | Higher VILI risk |
>20 J/min | Significant VILI risk |
Why Important?
A patient may have: Safe VT or Safe Pplat but High RRo r High PEEP leading to excessive energy delivery.
Mechanical power captures the combined effect of all ventilator settings.
HFNC and BiPAP in ARDS
Mild–moderate hypoxemic ARDS
→ HFNC 40–60 L/min(FLORALI trial)
→ Adjust FiO₂ to maintain appropriate SpO₂
→ Check ROX index
→ Consider awake prone positioning in appropriate patients
If respiratory distress remains significant despite HFNC
→ Consider NIV/BiPAP(RECOVERY-RS trial)in a closely monitored ICU setting in a cooperative patient without contraindications.check HACOR score.
- Awake proning can be used with high flow nasal cannula (HFNC), CPAP, or BiPAP.
Severe ARDS / rapidly worsening patient
→ Do not persist with HFNC/BiPAP simply to avoid intubation.
→ Proceed to endotracheal intubation and lung-protective mechanical ventilation when there is failure of noninvasive support.
Adjunctive Therapies
Therapy | Role |
Inhaled nitric oxide | risks of methemoglobinemia and acute kidney injury Temporary oxygenation improvement therefore can be used in erasing ARDS patient. |
inhaled epoprostenol | Evidence lacking |
Complications
- Secondary infections
- ICU myopathy
- Delirium
- Fibrosis
ARDS Mortality Causes
Most deaths due to:Sepsis,Multi-organ failure NOT hypoxemia alone.
Emerging Concepts
ARDS Phenotypes
Two biological phenotypes identified:
Phenotype | Features |
Hyperinflammatory | High cytokines, worse outcome |
Hypoinflammatory | Better prognosis |
Precision Medicine
Future therapy may involve:
- Biomarker-guided treatment
- Personalized ventilation
Trials in ARDS
Trial | Finding |
ARDSNet ARMA | Low tidal volume reduces mortality |
PROSEVA | Prone positioning improves survival |
ACURASYS | Early paralysis helpful |
FACTT | Conservative fluids beneficial |
EOLIA | ECMO for refractory ARDS |
Reference
1. Irwin & Rippe’s Intensive Care Medicine (9th Edition)
Lilly CM, Kelly WF, Irwin RS, Boyle WA III, editors. Irwin and Rippe’s Intensive Care Medicine. 9th ed. Philadelphia: Wolters Kluwer; 2023.
2. The Washington Manual of Critical Care (4th Edition)
Kollef MH, Despotovic V, Kraft BD, McDonald RK, Nguyen N, editors. The Washington Manual of Critical Care. 4th ed. Philadelphia: Wolters Kluwer; 2024.
3.Ohs manual of critical Care